Uncategorized


Sloppy medical records aren’t just jeopardizing patient care. They’re preventing scientists from finding new cancer treatments. “The data are trapped.
By Gina Kolata
Dr. Nikhil Wagle thought he had a brilliant idea to advance research and patient care.
Dr. Wagle, an oncologist at the Dana Farber Cancer Institute in Boston, and his colleagues would build a huge database that linked cancer patients’ medical records, treatments and outcomes with their genetic backgrounds and the genetics of their tumors.
The database would also include patients’ own experiences. How ill did they feel with the treatments? What was their quality of life? The database would find patterns that would tell doctors what treatment was best for each patient and what patients might expect.
The holdup, he thought, would be finding patients. Instead, the real impediment turned out to be gathering their medical records.
In the United States, there is no single format used by all providers, and hospitals have no incentive to make it easy to transfer records from one place to another. The medical records mess is hobbling research and impeding attempts to improve patient care.
“Data are trapped,” said Dr. Ned Sharpless, director of the National Cancer Institute. “This is a huge problem. It is phenomenally important.”
The cancer institute has invested millions of dollars into determining the genetic sequences of patients’ tumors, and researchers have found thousands of genes that seem to drive tumor growth.
But until patients’ medical records are linked to the genetic data, life-or-death questions cannot be answered.
“What drug did they get? Did they respond? Did they survive? Were they cured?” Dr. Sharpless asked.
The federal government has mandated uniform standards for electronic health records. “At this point, they are not to a level that helps with the detailed clinical data that we need for the scientific questions we want to ask,” Dr. Wagle said.
A few private companies are trying to tackle the problem. Flatiron Health, just bought by Roche, has obtained about 2.2 million records of cancer patients from medical centers and made them available for research after stripping them of identifiable information.
But Flatiron must employ 900 nurses and certified tumor registrars, people with master’s degrees in coding data, to put it all into a usable form.
“About 50 percent, if not more, of the critical details we need for research are trapped in unstructured documents,” said Dr. Amy Abernethy, the company’s chief medical officer.
“They are in PDFs. Maybe a doctor put in a note by hand, maybe a doctor typed it. That note became a narrative. It is not something that can easily be put into a spreadsheet.”
Dr. Sharpless worries that the data acquired by companies like Flatiron will not be readily available to researchers. But if the companies manage to solve the medical records problem cheaply, he said, “we’d like to work with them to figure out how to liberate the data.”
Dr. Wagle is making data from medical records and patients’ experiences public as he gets them. After 2 1/2 years, though, he is disappointed by how little there is to share.
The patient who inspired his project had a lethal form of thyroid cancer. She was expected to die in a few months. In desperation, doctors gave her a drug that by all accounts should not have helped.
To everyone’s surprise, her tumors shrank to almost nothing, and she survived. She was an “extraordinary responder.”
Why? It turned out that her tumor had an unusual mutation that made it vulnerable to the drug.
And that got Dr. Wagle thinking. What if researchers had a database that would allow them to find these lucky patients, examine their tumors, and discover genetic mutations that predict which drugs will work?
And what about those who were not helped by standard treatments? Could they be identified and spared treatments that will not work?
What researchers needed was a huge database that collected clinical and genetic data, along with patients’ descriptions of their experiences. Those narratives are crucial, Dr. Wagle said, but they are absent from the commercial databases like Flatiron’s. Those comprise anonymous patient data, making it impossible to ask the patients themselves how they fared.
Dr. Wagle decided to build a database, starting with metastatic breast cancer, his specialty. There are about 155,000 metastatic breast cancer patients in the United States. He would use social media, online forums and advocacy groups to reach out to patients for their records.
The Metastatic Breast Cancer Project began in October 2015. Patients have been eager to join, and advocacy groups enthusiastically signed on. So far, the project includes 4,400 women.
Determining the genetic sequences of their tumors and of their healthy cells was straightforward — “the easy part,” Dr. Wagle said.
Gathering their medical records was another story. The data exist in all sorts of formats, and crucial information may be missing altogether.
Simply getting the records delivered, in whatever format, has been a nightmare. Records usually arrive as faxes or via snail mail.
“Even though the patients are saying, ‘I have consented for you to obtain my medical records,’ there is no good way to get them,” Dr. Wagle said.
He hired half a dozen people to work full-time on the project, and corralled doctors and other experts to help part-time. It can take hours to go through a single medical record.
Mary McGillicuddy, who works full-time on the project, explained the system. When patients enroll, they tell the investigators where they were treated, where they had biopsies, where they had scans, and where they had medical procedures.
They give Ms. McGillicuddy and her colleagues permission to request their records. Ms. McGillicuddy faxes requests for records to each medical institution that treated a patient, or diagnosed or sequenced her cancer.
Startlingly, faxing “is the standard,” Ms. McGillicuddy said, for medical records requests.
The process can be frustrating. Fax numbers can be out of date. Some medical centers will not accept electronic patient signatures on the permission forms.
Sometimes, the medical centers just ignore the request — and the second request. In the end, Ms. McGillicuddy said, the project gets fewer than half the records it requests.
Then comes the laborious task of extracting medical information from the records and entering it into the database. A faxed medical record may be 100 or 200 pages long.
So far, the breast cancer project has received 450 records for 375 patients. (Each patient tends to have more than one record, because the women typically are seen at more than one medical center.)
“Patients are incredibly engaged and excited,” Dr. Wagle said. But for the records problem, “right now there isn’t a good solution.”
An earlier version of this article described incorrectly Dr. Amy Abernethy’s role at Flatiron Health. She is its chief medical officer, not its founder. In addition, the article misstated the number of medical records obtained by the company. The figure is 2.2 million, not 1 million.
Article link: https://www.nytimes.com/2018/05/21/health/medical-records-cancer.html
VA Video Connect eases access for patients seeking appointments

VA Video Connect can be used by any veteran who has video-capable technology — such as a smartphone, tablet or computer.
For many veterans, communicating with a doctor in real time will now be as convenient as putting a new app on their smartphone, tablet or personal computer.
VA Video Connect, which the U.S. Department of Veterans Affairs (VA) began piloting in 2017, is now being rolled out to veterans across the country. The service enables veterans to interact with their physicians using a secure video connection to address nearly any issue that does not require an in-person visit.
The app can be used by any veteran who has video-capable technology — such as a smartphone, tablet or computer — a reliable internet connection, and access to a VA provider who uses the service. The VA began rolling out Video Connect in July 2017; as of April 20, 4,500 VA providers had used it to communicate with more than 22,500 veterans. The VA hopes that increased use of Video Connect will help relieve some of the agency’s wait time and access issues.
The new service has already demonstrated its capabilities. When VA Video Connect was being piloted last year, its introduction coincided with the devastation left behind by hurricanes Harvey and Irma. Video Connect enabled VA physicians to remotely get veterans the care they needed, underscoring its potential to reach patients unable to physically travel because of their disability or distance from their doctor.
The service is also valuable to veterans who have mental health issues. It can put patients in virtual touch with psychiatrists and counselors, bypassing the often long waits for appointments. “Having that availability is important, whether in person or through telemedicine,” says Garry Augustine, executive director of DAV (Disabled American Veterans), a nonprofit organization that provides services for and lobbies on behalf of more than a million wounded veterans. “It’s a good option for times when a vet needs to be able to talk to a professional quickly,” Augustine says.
Telemedicine is not a new service for the VA. According to a spokesperson, the department pioneered telemedicine nearly 60 years ago, using closed-circuit television to connect a mental health therapist with a group of veterans gathered in a remote location. By 2006, advancements in technology allowed the VA to enable physicians to use telemedicine to screen veterans in remote medical facilities for conditions such as diabetic eye disease.
Today, the VA offers telemedicine services in more than 50 clinical specialty areas, such as wound care and dermatology. VA physicians conduct millions of remote visits each year. In fiscal year 2017, more than 727,000 veterans used VA tele-health services in medical facilities, representing more than 2.18 million episodes of care. Now that access is spreading to veterans’ personal devices.
VA Video Connect works on any device that has an internet connection, a web camera, a microphone and speakers. It is available in the Apple App Store for iPhones and iPads. On personal computers and Android or Windows mobile devices, VA Video Connect operates as a web-based app, and it does not require an app download. To determine whether a device is compatible with VA Video Connect, veterans can visit the VA Video Connect test site.
Article link: https://www.aarp.org/home-family/voices/veterans/info-2018/va-video-connect-health-app.html
David I. Rosenthal, M.D., and Abraham Verghese, M.D,

Supplementary Material
| Disclosure Forms | 115KB |
References (5)
-
Czernik Z, Lin CT. A piece of my mind: time at the bedside (computing). JAMA 2016;315:2399–2400
-
Chi J, Verghese A. Clinical education and the electronic health record: the flipped patient. JAMA 2014;312:2331–2332
-
Verghese A. Culture shock — patient as icon, icon as patient. N Engl J Med 2008;359:2748–2751
-
Mata DA, Ramos MA, Bansal N, et al. Prevalence of depression and depressive symptoms among resident physicians: a systematic review and meta-analysis. JAMA 2015;314:2373–2383
-
Friedberg MW, Chen PG, Van Busum KR, et al. Factors affecting physician professional satisfaction and their implications for patient care, health systems, and health policy. Santa Monica, CA: RAND, 2013 (http://www.rand.org/pubs/research_reports/RR439.html).
Close References
Citing Articles (9)
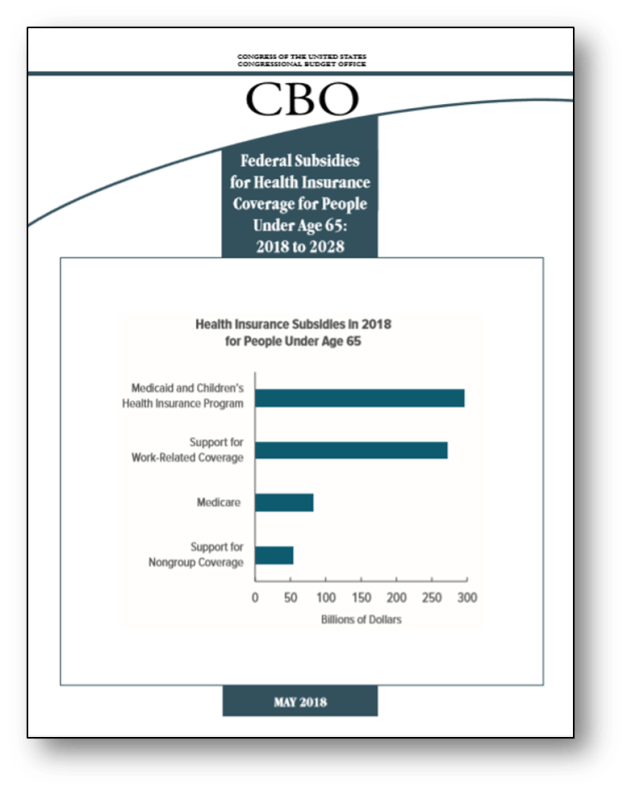



Toplines
- Third-party payment programs make health insurance affordable for low-income consumers by paying the health plan premium costs not covered by the ACA’s tax credits
- Third-party payment programs not only help low-income Americans afford marketplace health coverage, they also reduce hospitals’ uncompensated care costs
Abstract
- Issue: Consumers’ concerns about affordability limit participation in ACA marketplaces. Funded by local hospital systems and run by independent nonprofits, third-party payment (TPP) programs improve affordability for low-income consumers by paying premium costs not covered by tax credits.
- Goal: To assess the potential of TPP to make marketplace coverage more affordable, without harming insurance risk pools.
- Methods: Interviews in May and June 2016 with program administrators, hospital systems, carriers, and consumer groups in five localities and the Washington State marketplace.
- Key Findings: The most effective local program reached 1,148 people, or 25 percent of all eligible marketplace enrollees. Other local programs served between 202 and 934 consumers; the Washington State program reached 1,133. Findings suggest that without TPP, numerous beneficiaries would have remained uninsured. Hospitals funding these programs reported net financial benefits, with declines in uncompensated care exceeding program costs. Carriers reported no adverse selection in these carefully designed programs. Conclusions: Widespread adoption of TPP could help additional low-income consumers obtain marketplace coverage. Hospitals’ financial gains from TPP programs make replication more feasible. However, broader policies, such as increased premium tax credits and cost-sharing reductions, are likely needed for major nationwide improvements to affordability.
Introduction
With roughly 20 million Americans gaining coverage under the Affordable Care Act (ACA), the United States has made enormous progress in reducing the number of uninsured.1 Nevertheless, 28.6 million people remained without health coverage in 2016,2 of whom an estimated 62 percent qualified for Medicaid or marketplace coverage.3 As of June 2015, only 35 percent of consumers eligible for advance premium tax credits — which lower monthly health insurance payments — had enrolled in marketplace plans.4 Research suggests that the most important obstacle to increased enrollment has been consumers’ belief that coverage is unaffordable.5
Currently, the future of the ACA remains unresolved, but the basic framework of the legislation could well remain intact. If so, stakeholders and policymakers will need to revisit these affordability concerns. A fully effective solution would likely include higher premium tax credits and cost-sharing reductions. Until such a solution is considered, more incremental strategies may be needed, like third-party payment (TPP) programs, through which health care providers pay low-income consumers’ share of enrollment costs.
History suggests that TPP programs can address low-income consumers’ affordability concerns on a large scale. Long before the ACA, Washington State’s Basic Health Program let nonprofit organizations pay the premium charges of eligible consumers using donations from safety-net providers. The state stopped most new enrollment in the early 2000s. Before then, this TPP initiative achieved significant gains, enrolling nearly a quarter of all 133,000 consumers who received subsidized coverage when the state’s Basic Health Program reached its high-water mark in 2001.6
Some carriers have expressed concerns that TPP programs could skew risk pools by triggering “adverse selection,” or disproportionately high enrollment of consumers with serious health problems. For example, carriers have raised concerns about health care providers increasing their payments for kidney dialysis and other high-cost conditions by steering patients who qualify for Medicaid or Medicare to nonprofit organizations, which in turn enroll the patients into marketplace plans that pay higher reimbursement rates.7 After seeing “problematic” effects on consumers and risk pools, the Centers for Medicare and Medicaid Services (CMS) circulated regulations in late 2016 limiting TPP programs that focus on dialysis patients.8 Those regulations soon became the subject of litigation,9 and a broader policy debate continues around TPP programs that serve patients with specific diagnoses.10
This issue brief focuses on different TPP programs: those that base eligibility on income rather than the presence of particular health conditions. Based on interviews conducted in May and June 2016 with nonprofit program administrators, hospital systems, carriers, and consumer groups in five localities and the Washington State marketplace, we examine whether income-based TPP programs can improve enrollment and retention without triggering harmful adverse selection.11 We also explore whether income-based TPP programs could be implemented on a much larger scale. For detailed information on our methods, see How We Conducted This Study.
Read more http://www.commonwealthfund.org/publications/issue-briefs/2018/may/third-party-payment-programs
Catherine H. MacLean, M.D., Ph.D., Eve A. Kerr, M.D., M.P.H., and Amir Qaseem, M.D., Ph.D., M.H.A.

Supplementary Material
| Supplementary Appendix | 937KB | |
| Disclosure Forms | 109KB |
References (5)
- Qaseem A, Snow V, Gosfield A, et al. Pay for performance through the lens of medical professionalism. Ann Intern Med 2010;152:366–369.
2. Berwick DM. Era 3 for medicine and health care. JAMA 2016;315:1329–1330.
3. Casalino LP, Gans D, Weber R, et al. US physician practices spend more than $15.4 billion annually to report quality measures. Health Aff (Millwood) 2016;35:401–406.
4. Higashi T, Shekelle PG, Adams JL, et al. Quality of care is associated with survival in vulnerable older patients. Ann Intern Med 2005;143:274–281.
5. Hemingway H, Crook AM, Feder G, et al. Underuse of coronary revascularization procedures in patients considered appropriate candidates for revascularization. N Engl J Med 2001;344:645–654.
Transforming Care focuses on new models of care, payment approaches, and patient engagement strategies that have the potential to reshape our delivery system to better meet the needs of the nation’s sickest and most vulnerable patients.
March 29, 2018 Issue
In Focus: Increasing Collaboration Among Physicians, Hospitals, and Postacute Providers to Reduce Variation and Spending
While many U.S. hospitals have concentrated on improving care transitions from hospital to home, far fewer have focused on the transition from hospitals to postacute care settings, including skilled nursing facilities. Increased awareness of variations in spending on postacute care and avoidable complications after hospital discharge — together with value-based payment arrangements — have prompted some physician groups, health systems, health plans, and postacute care providers to collaborate. Among their methods: assessing patients’ risk and identifying the most appropriate setting for them to recover and offering education to help patients regain their functionality and stay well. Better data about what works best for different patients and more aligned financial incentives among acute and postacute care providers could further these efforts.
By Martha Hostetter and Sarah Klein
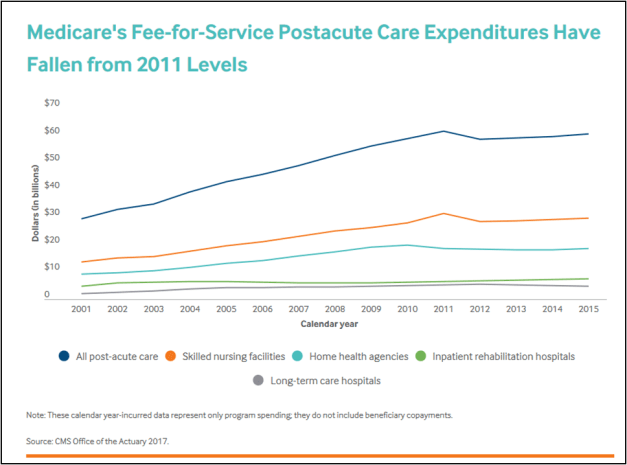
The Institute of Medicine’s 2013 study of Medicare spending upended a common assumption about the biggest drivers of regional variation: it was not hospital use that accounted for the largest the differences in spending across regions, but what happened after patients emerged from hospitals and began making use of skilled nursing facilities (SNFs) and home health care. The report also traced the dramatic rise in spending on SNF use and other types of postacute care, which more than doubled from 2001 to 2011, making it the fastest-growing sector of health care.1
The rise in the use of postacute care can be traced to Medicare’s decision in the 1980s to stop paying hospitals on a fee-for-service basis and instead make payments based on patients’ diagnoses, not how long they stay. This, together with the increased prevalence of capitated payments under managed care in the 1990s, led hospitals to reduce lengths of stay. Both factors fueled demand for postacute care providers — which include skilled nursing facilities (SNFs), home health agencies, inpatient and outpatient rehab facilities, and long-term hospitals — to help patients recover after surgery or acute illness and return home.2 Demand for postacute care also increased as a function of the aging of the U.S. population and the increasing prevalence of chronic and disabling conditions, which complicate recovery.3 About two of five Medicare beneficiaries end up needing some form of postacute care after a hospitalization.4
Read article: http://www.commonwealthfund.org/publications/newsletters/transforming-care/2018/march/in-focus

Findings from the Commonwealth Fund Affordable Care Act Tracking Survey, February–March 2018
Tuesday, May 1, 2018
By Sara R. Collins, Munira Z. Gunja, Michelle M. Doty and Herman K. Bhupal
Toplines
-
About 4 million working-age people have lost insurance coverage since 2016
-
The uninsured rates among lower-income adults rose from 20.9 percent in 2016 to 25.7 percent in March 2018
The marked gains in health insurance coverage made since the passage of the Affordable Care Act (ACA) in 2010 are beginning to reverse, according to new findings from the latest Commonwealth Fund ACA Tracking Survey. The coverage declines are likely the result of two major factors: 1) lack of federal legislative actions to improve specific weaknesses in the ACA and 2) actions by the current administration that have exacerbated those weaknesses. These include the administration’s deep cuts in advertising and outreach during the marketplace open-enrollment periods, a shorter open enrollment period, and other actions that collectively may have left people with a general sense of confusion about the status of the law. Signs point to further erosion of insurance coverage in 2019: the repeal of the individual mandate penalty included in the 2017 tax law, recent actions to increase the availability of insurance policies that don’t comply with ACA minimum benefit standards, and support for Medicaid work requirements.
In this post, and another soon to follow, we will look at people’s recent experiences with their insurance coverage and the affordability of their health insurance and health care.1 The ACA Tracking Survey is a nationally representative telephone survey conducted by SSRS that tracks coverage rates among 19-to-64-year-olds and has focused in particular on the experiences of adults who have gained coverage through the marketplaces and Medicaid. The latest wave of the survey was conducted between February and March 2018. Forthcoming results from large federal surveys like the National Health Interview Survey will shed more light on the trends our survey has identified.2
Findings
Uninsured Rate Among Working-Age Adults Is Up Significantly Since 2016
The uninsured rate among working-age people — that is, those who are between 19 and 64 — is at 15.5 percent, up from 12.7 percent in 2016, meaning an estimated 4 million people lost coverage (Tables 1 and 2). Rates were up significantly compared with 2016 among adults with lower incomes — those living in households earning less than 250 percent of poverty (about $30,000 for an individual and $61,000 for a family of four).
Read full Article: http://www.commonwealthfund.org/publications/blog/2018/apr/health-coverage-erosion

