healthcarereimagined

Envisioning healthcare for the 21st century

  • About
  • Economics

Can technology restore humanity to healthcare? – Healthcare IT News

Posted by timmreardon on 12/19/2018
Posted in: Uncategorized. Leave a comment

With EHR frustrations at a boiling point and physician burnout at epidemic levels, it’s time to rethink the way IT is designed, developed and deployed to better enable a human touch, says one clinician.

By Mike MiliardDecember 07, 2018

HIT News

“At its core, technology would seem to be the antithesis of humanity,” said Dr. Chris Derienzo, chief quality officer at Asheville, North Carolina-based Mission Health System. “It doesn’t feel, it doesn’t think and it can’t see the humanity of the person in front of it,” he explained.”
Ask physicians how the feel about electronic health records, or read Atul Gawande’s recent New Yorker feature, “Why Doctors Hate Their Computers,” and it’s apparent that most healthcare professionals’ relationship with technology is ambivalent at best.
“It’s tempting to say there’s no way we can build or leverage technology in order to restore some humanity to the practice of medicine,” said Derienzo. “But I think that’s fundamentally a wrong assumption.”
At HIMSS19 in Orlando, in one of the new TED Talk-style SPARK Sessions, titled “Humanity and Technology in Medicine: Antithetic or Symbiotic?” Derienzo will explain why.
The reason technology seems to pull us away from people, rather than bring us together, mostly boils down to “how we’ve designed it and what we’ve designed,” Derienzo said. But rethinking both of those, IT could be repositioned in a way where it enhances, rather than detracts, from the clinician and patient experience.
With funny personal anecdotes and real-life case studies, he’ll show how technology, properly deployed, can restore joy to healthcare – helping burnt-out physicians better engage person to person, enabling them to practice at the top of their license and use their skills to solve complex challenges
“If we focus on the right types of technology, and we build it right, then we can actually use it to empower people to do more of the things that only people can do in healthcare,” said Derienzo.
How technology is designed, and what it’s used for, plays a big role in how well it is liked by its end-users. Consider tech that’s intentionally created connect people, such as telemedicine. “We see much more positive reaction to it.”
EHRs, on the other hand, were not designed with joy in mind. They were developed under certain conditions, with necessary check-the-box functionalities related to regulatory compliance and billing capture.
And they were “based on a world where we took what we did on paper then did the same thing on computers,” said Derienzo. They effectively ignored a lot of the human factor elements for how to design a way to document and record care electronically.”
But EHRs are only one challenge, he said. “Our monitors are another. How we use algorithms is another very important one.”
Derienzo predicts that “our electronic documentation will evolve drastically over the next few years as we move away from this built environment and toward a world where human factors matter a whole lot more.”
In the meantime, he sees one technology doing a lot to return humanity to healthcare. One that may seem ironic, to say the least, given the trepidations many have about its potential to disrupt and displace: artificial intelligence.
“AI stands positioned to be one of the core technological advances that allows us to return humanity to healthcare,” he said.
For example, he explained, “we’ve built a machine learning model at Mission Health and we’ve now gotten it fully up and running. Its purpose is to help risk-stratify patient who are case managers need to focus on. To serve them, not only by a ranked-ordered list but a concept as to why our model thinks they may be at a high risk of being readmitted.”
That’s a fairly AI application, “but its purpose is to pull out things that people don’t have to be doing so now my care manager team can spend less time wondering who to focus on and more time actually focusing on people,” said Derienzo.
Ditto with radiology, he said: “I don’t think that reading a thousand normal chest X-rays brings radiologist a ton of joy. But doing the really complex work – is it this, is it that? – is what they enjoy. How do we bring the expertise and brains of these terrific musculoskeletal and neuroradiologists tp the things we actually need them to be doing? That is how something like AI can actually empower humans.
The practice of medicine is an ancient art, and one that’s long depended on the power of human interaction, he explained.
“At one point that was all we had – other than leeches and bloodletting, all we had was the ability to interact with our patients one on one and be human with them,” said Derienzo.
“We’ve vastly improved our ability to care since then, but in some ways we’ve lost an appreciate for that aspect of a clinician patient relationship,” he explained. “My fervent hope is that once we get this right, we’ll actually be returning, somewhat, to a place where it’s that person to person relationship that’s the most valuable part of our day.”
Chris Derienzo’s HIMSS19 SPARK session, “Humanity and Technology in Medicine: Antithetic or Symbiotic?” is scheduled for Tuesday, February 12, from 3-3:30 p.m. in room W300.

Article link: https://www.healthcareitnews.com/news/can-technology-restore-humanity-healthcare
Topics: Artificial Intelligence, Clinical, Electronic Health Records (EHR, EMR)

Intelligent Machines – Nine charts that really bring home just how fast AI is growing – MIT Technology Review

Posted by timmreardon on 12/19/2018
Posted in: Uncategorized. Leave a comment

Artificial intelligence is booming in Europe, China, and the US, but it’s still a very male industry.

by Will Knight  December 12, 2018

MIT 1 aicharts

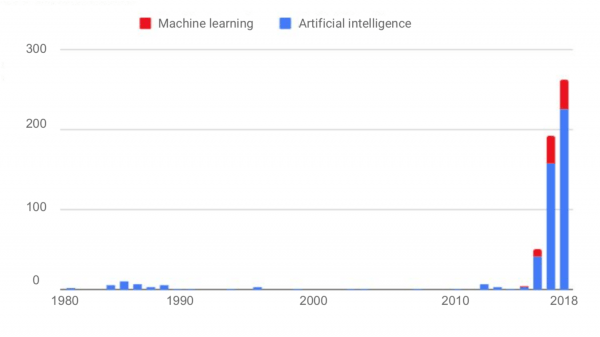
With so much hype surrounding artificial intelligence today, it can be difficult to know where things actually stand. Fortunately, a report (.pdf) issued by a group of AI policy researchers today collates a range of data that helps capture the state of the AI boom.
Recommended for You

The authors, from MIT, Stanford, and Harvard as well as nonprofits including OpenAI, look at investments, hiring, papers and patents, and even mentions of AI at government meetings. Here are some take-aways.

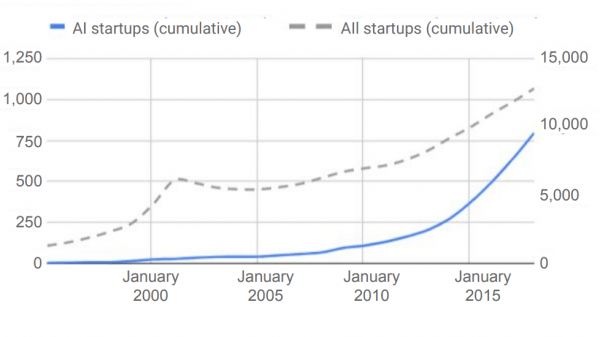
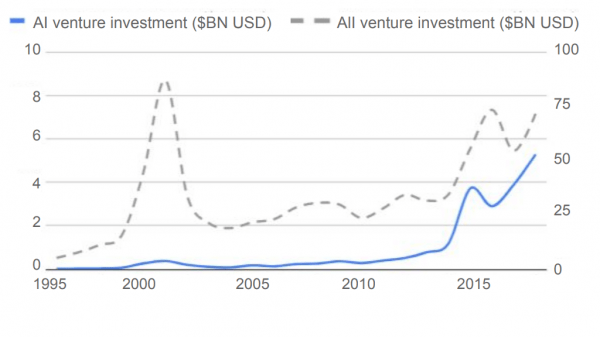
1. AI is being commercialized at a dizzying pace.

MIT Ai Chart 2

The amount of money being poured into AI startups is remarkable. The number of AI startups (top) is shown on the left, compared with total startups on the right. AI investment (below) is shown on the left, compared with total investments on the right. This speaks to huge opportunities to use machine learning in different industries, but also to a market that is hyped and overheated.

MIT AI Chart 3

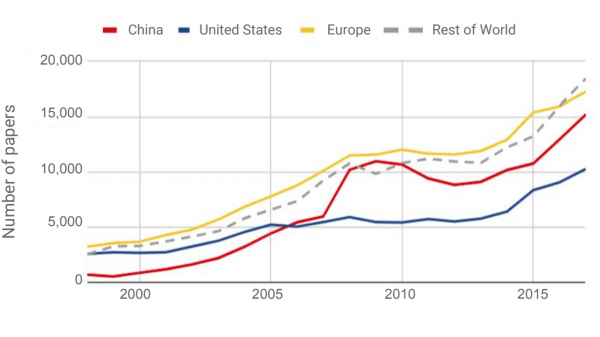
2. The focal points are China and the US, but also Europe.

Much has been made of China’s rising AI prowess (see “China’s AI awakening”) and its growing rivalry with the US. As the data shows, Europe is also a huge hub of AI activity. But it seems that three main centers of power are emerging.

MIT AI Chart 4

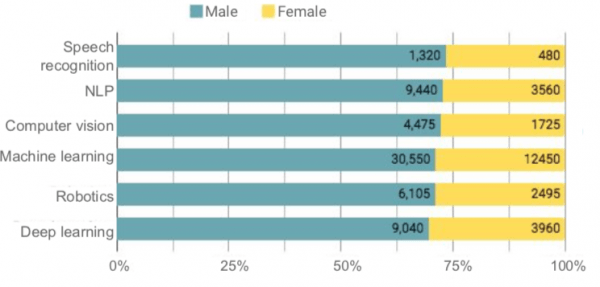
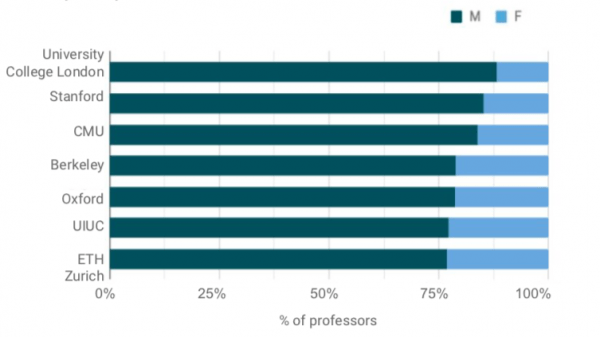
3. There are still far more men in the field than women.

MIT AI Chart 5

Many researchers have pointed to the inadequate number of women and racial minorities in AI research. The new report offers some data to back that up, showing a shortage of women among applicants for AI-related jobs (top) and as a percentage of people in AI teaching roles (bottom).

MIT AI Chart 6

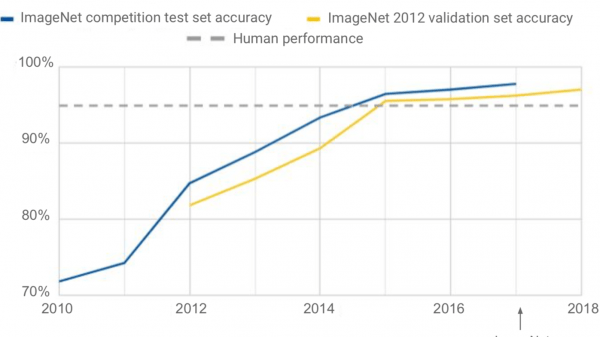
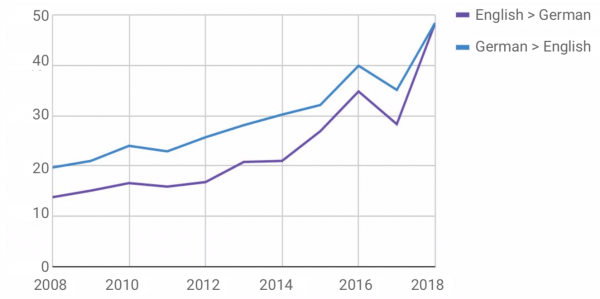
4. The state of the art is improving fast.

MIT AI Chart 7

The report includes several measures of technical progress, including the accuracy of object recognition in images, measured against average human performance (top), and the accuracy of machine translations of news articles, measured using a score assigned by human judges (bottom). These don’t mean that the field is getting closer to developing a human-level AI, but they show how key techniques have been honed in recent years.

MIT AI Chart 8

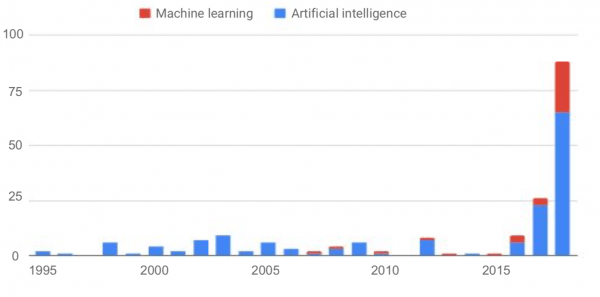
5. Artificial intelligence is a political issue.

MIT AI Chart 9

Mentions of artificial intelligence and machine learning in the US Congress (above) and the UK Parliament (below) have exploded in the past few years. This reflects a growing awareness of the technology’s economic and strategic importance (see “Canada and France propose an international panel on AI”).

MIT AI Chart 10

For more info, and to find the data itself, check out the AI Index site.

Article link: https://www.technologyreview.com/s/612582/data-that-illuminates-the-ai-boom/

Many smaller providers regretting EHR switches – Healthcare IT News

Posted by timmreardon on 12/19/2018
Posted in: Uncategorized. Leave a comment

Black Book survey shows that some were wooed by brand names, instead of seeking core functionalities that give ROI – and wish they’d gotten more bang for their buck.

By Benjamin Harris  December 11, 2018

HC IT IT-Frustration-HITN

Findings from a recent Black Book survey shouldn’t be much of a surprise to anyone in the healthcare IT world: changing electronic vendors is expensive, time-consuming and full of hidden challenges.

Bigger health systems usually weather the disruption more easily and come out happier on the other end. Smaller providers, however, struggle to cope with hidden costs, user frustration, and longer than expected downtime, among other things.

Brand-name recognition and overeager sales pitches hid some of the most significant challenges providers encountered. Black Book found that 71 percent of providers who switched EHRs saw a drop in interoperability.

WHY IT MATTERS
EHRs are expensive, and also mandatory. When they don’t work well or when physician buy-in to the system is lackluster, it eats into revenue which can already be strained to recoup on the cost of an EHR implementation.

Cost overruns or implementation delays caused temporary or permanent layoffs for 22 percent of those responding in the survey, not to mention additional headaches for the remaining staff and lost more money for the system.

Finally, clinician burnout, an already worrisome trend, can be exacerbated by changing EHR systems, something an astounding 98 percent of respondents said wasn’t a part of the conversation as they switched EHR systems.

“No other industry spends so much, per unit of IT, on the part of the business that is shrinking the fastest and holds little growth as hospital inpatient revenues,” said Doug Brown, president of Black Book.

THE LARGER TREND
Black Book finds the majority of financially threatened healthcare systems regret switching EHRs – so changing horses mid-race might not be the first move a smaller or struggling provider might want to make. The survey notes that changing providers is a risk that many small healthcare systems are unable to make work to their benefit in the long run.

Instead, taking steps such as recognizing the impact of physician burnout, or directing more focus on achievable financial goals such as interoperability or greater functionality may be a smarter tactic.

ON THE RECORD
“In retrospect, mid-market system CIOs spent a lot of money focusing on functionality and incentive-dollar achievement, thus many did not appropriately approach long-term value by dealing with basic issues, such as departmental workflows, usability, interoperability and data-sharing standards,” said Brown.

“We found the majority (69 percent) of struggling hospital systems in 2018 that are dealing with very tight margins – or even losing money – regret their IT choices, which still have them teetering between being able to stay open or having to close,” he said.

Article link: https://www.healthcareitnews.com/news/many-smaller-providers-regretting-ehr-switches

Benjamin Harris is a Maine-based freelance writer and and former new media producer for HIMSS Media.
Twitter: @BenzoHarris.

Topics:

Electronic Health Records (EHR, EMR), Financial/Revenue Cycle Management, Workflow

Defense Health Care: DOD Should Demonstrate How Its Plan to Transfer the Administration of Military Treatment Facilities Will Improve Efficiency – GAO

Posted by timmreardon on 12/17/2018
Posted in: Uncategorized. Leave a comment

What GAO Found
The Department of Defense’s (DOD) June 2018 plan addressed the four statutory elements for the transfer of the administration of the military treatment facilities (MTFs) from the military departments to the Defense Health Agency (DHA). Specifically, the plan provided information on (1) how the DHA will take administrative responsibility of the MTFs; (2) efforts to eliminate duplicative activities; (3) efforts to maximize efficiencies in the DHA’s activities; and (4) reductions of headquarters-level military, civilian, and contractor personnel. DOD dedicated most of the plan to describing the governance structure of the proposed administrative framework and to describing the timeline for a phased transfer of the approximately 457 MTFs to the DHA by October 1, 2021. Initially, DOD was to transfer responsibility for the administration of the MTFs to the DHA by October 1, 2018. However, Congress in the National Defense Authorization Act (NDAA) for Fiscal Year 2019 amended the law to allow, among other things, DOD to complete the transfer by September 30, 2021.
DOD has taken key steps in its June 2018 plan to improve the effectiveness and efficiency of the administration of MTFs. However, DOD’s plan has two weaknesses that could be mitigated with additional information.

Specifically, DOD excluded 16 operational readiness and installation-specific medical functions from consideration for transfer to the DHA. DOD did not define or analyze the potential effect of excluding these functions, which include dental care, substance abuse, and occupational health. Senior officials from the DHA and the Assistant Secretary of Defense for Health Affairs acknowledged that transferring the dental care function, for example, from the military departments to the DHA could potentially reduce duplicative activities.
DOD’s plans to achieve the stated goal of reducing headquarters-level personnel, including contractor personnel, by 10 percent are unclear. In its June 2018 plan, DOD states that the DHA will experience personnel growth during each phase of the transition, but that it expects to reduce headquarters-level personnel by 10 percent by 2021. However, the plan does not provide specific details about how DOD will achieve the established goal of reducing headquarters-level personnel by 10 percent while the DHA experiences personnel growth. Further, the plan does not address whether and how contractor personnel factor into the reduction. This lack of clarity exists because DOD has not validated headquarters-level personnel requirements or conducted a comprehensive review to identify the least costly mix of military, civilian, and contractor personnel to meet the validated requirements.
Until DOD takes action to resolve these two weaknesses, DOD will likely not be well positioned to reduce or better manage duplication and improve efficiencies, including reducing headquarters-level personnel across the Military Health System. Furthermore, Congress will lack important information to determine the extent to which the transfer of the administration of the MTFs to the DHA is being planned and implemented effectively and efficiently.
Why GAO Did This Study
In fiscal year 2017, DOD provided health care to 9.4 million beneficiaries, including servicemembers, retirees, and their families at a cost of $43 billion. For more than a decade, partially in response to congressional mandates, DOD has worked to address inefficiencies in the Military Health System to control costs.
To further achieve efficiencies, the NDAA for Fiscal Year 2017 required DOD to develop an implementation plan that addressed four elements related to transferring the administration of the MTFs to the DHA. DOD issued the plan in June 2018.
The NDAA also included a provision for GAO to review the plan. GAO determined whether (1) DOD’s plan included the statutory elements related to the transfer of administration of the MTFs to the DHA and (2) additional information would be useful to demonstrate that the plan will reduce or better manage duplication and improve efficiencies. GAO assessed DOD’s plan against the required elements and, where appropriate, considered the extent to which the plan provided detailed information related to key change management practices identified in past GAO work.
What GAO Recommends
GAO recommends that DOD define and analyze the 16 operational readiness and installation-specific medical functions for duplication, validate headquarters-level personnel requirements, and identify the least costly mix of personnel. DOD concurred with all three recommendations and noted actions it was taking to address each one.
For more information, contact Brenda S. Farrell at (202) 512-3604 at or farrellb@gao.gov.

GAO DHA 1

Study: VA hospitals outperform nearby healthcare facilities – UPI

Posted by timmreardon on 12/17/2018
Posted in: Uncategorized. Leave a comment

By Tauren Dyson

UPI-1

Dec. 12 (UPI) — With about nine million veterans throughout its system, U.S. Veterans Administration, or VA, hospitals may deliver better medical care than other hospitals, according to a study.

The new findings are based on data from 15 data outcome measurements from the Centers for Medicaid and Medicare Studies, or CMS, on VA and non-VA hospitals, including 30-day risk-adjusted mortality rates for common diseases like acute myocardial infarction, COPD, heart failure and pneumonia. Researchers also analyzed 11 additional patient safety indicators.

Based on those factors, the study’s researchers determined that VA hospitals would likely provide better medical care than local hospitals and health facilities.

“We wanted to take a closer look at local healthcare markets and specific health conditions because if you’re a veteran deciding where to seek treatment what you’re really concerned with are the outcomes at your local VA,” Dr. William Weeks, a professor at the Dartmouth Institute, said in a press release.

The researchers used the indicators to gauge various VA and non-VA hospitals within 306 hospital referral regions. For head-to-head comparisons, they confined the examination to 121 regions that had least one VA hospital and one non-VA hospital.

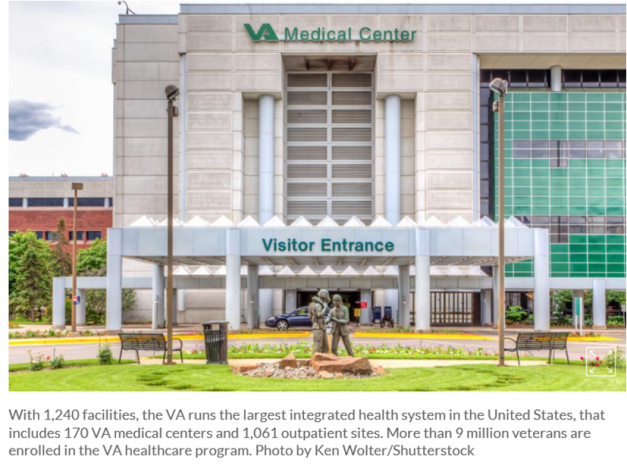
With 1,240 facilities, the VA runs the largest integrated health system in the United States, including 170 VA medical centers and 1,061 outpatient sites. More than 9 million veterans are enrolled in the VA healthcare program.

The study doesn’t account for all quality measures, and VA officials in the past have struggled to clean up the perception that the federal health care provider gives poor quality service.

In February, to address those quality issues, the VA announced a four-point plan to step up performance at low-performing facilities that included: national accountable leadership, comprehensive analysis and identification of improvement targets, and provision of national resources for improvement and accountability for results.

“President Trump has made it clear that our Veterans deserve only the best when it comes to their healthcare, and that’s why we are focusing on improving our lowest performing facilities nationwide,” VA Secretary David Shulkin said in February. “We will employ tight timelines for facilities to demonstrate improvement, and if low performance persists, we will make swift changes — including replacing facility leaders — until we achieve the rapid improvements that Veterans and taxpayers expect from VA.”

Earlier this year, the RAND Corporation also put care at the VA on par with other health providers.

The study acknowledges that, in some markets, non-VA hospitals provided better quality but, overall, VA hospitals provide better care.

“Our findings suggest that, despite some recent negative reports, the VA generally provides truly excellent care,” Weeks says. “If that is the case, outsourcing VA care to non-VA settings solely for patient convenience should be reconsidered.”

Read more: https://www.upi.com/Health_News/2018/12/12/Study-VA-hospitals-outperform-nearby-healthcare-facilities/1291544633966/#ixzz5Zxo83Yze


The silent shapers of healthcare services – McKinsey

Posted by timmreardon on 12/08/2018
Posted in: Uncategorized. Leave a comment


McKin1
The US healthcare services industry is at a tipping point, but who—or what—is driving the undercurrents of change?

Over the past five years, institutional investors have been quietly shaping parts of the healthcare industry. Private equity (PE) investors, for example, have begun to consolidate several markets, including ambulatory surgery, hospitalist staffing, and home health, undertaking more than $50 billion in total transactions.

Institutional investors’ focus on healthcare services—healthcare delivery and its enablers—is likely to continue, given industry trends. Ongoing growth in health expenditures, the degree of medical waste, and industry fragmentation signal high upside potential. Furthermore, the impact on the industry could be even greater in coming years. Institutional investors have been learning from their experience and will likely be using those lessons as they inject hundreds of billions in capital into healthcare in the next five years. These new investments have the potential to drive structural shifts in ways that are more direct and proactive than have been used before.

Health systems must decide how they want to respond—inaction is no longer an option. As they consider their responses, the systems need to answer two questions: Do they want to shape the industry on their own or alongside the institutional investors? And, how can they transform their business models to be sustainable as the industry evolves?

How active have investors been, and will it continue?

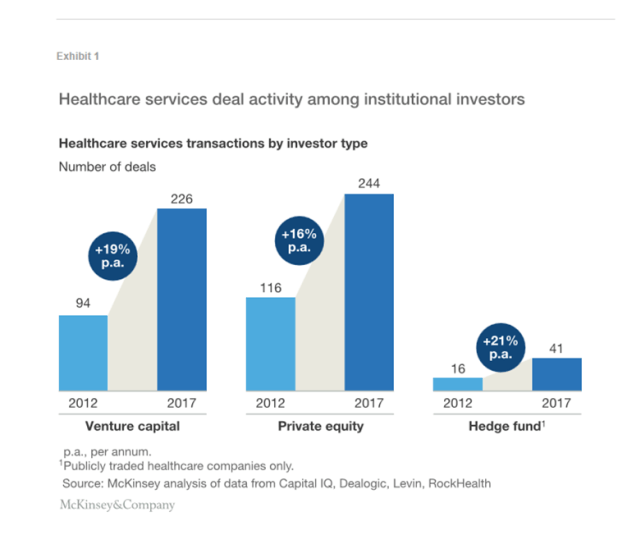
The degree of institutional investing in healthcare has accelerated. The number of deals has grown at a compound annual growth rate of 18% since 2012—PE, venture capital (VC), and hedge fund investors announced about 225 deals in 2012 but more than 510 in 2017.1 Each of these investor types has increased both its number of deals and share of overall healthcare investments. The capital inflow has been accompanied by high expectations for the return on invested capital (ROIC) and time frame within which returns would be achieved. These expectations have created tension with healthcare service providers and have shifted the providers’ expectations about how to deliver services and optimize operations to remain competitive, resulting in higher performance levels.

Because of the sums involved, institutional investors are now proactively shaping business models and submarkets within healthcare services. Exhibit 1 illustrates the magnitude of the fund flows.
McKin2
Over the past five years, annual returns on investments in healthcare services have averaged about 10%,2 but some investments have paid off better than others. Multiple investors had predicted increased demand for healthcare services and changes in market dynamics following passage of the Affordable Care Act (ACA). Those who have kept their money focused primarily on those themes have not fared as well as those who refined their view and shifted their investments in response to changes in the industry. Nevertheless, institutional investors have been able to raise additional funds. Several factors suggest the capital inflow from institutional investors will continue.

Demand dynamics remain favorable.

Between 2012 and 2016, total overall health­care EBITDA grew faster than did the combined EBITDA of the top 1,000 US companies.3 Growth in both the senior population and number of patients with chronic disease is likely to create a sustained increase in service demand. Healthcare spending in the United States is projected to rise by about 6% per annum through 2025 (assuming current care delivery trends continue).4

Economies-of-scale opportunity is clear.

Most healthcare service providers remain subscale and fragmented. The top five health systems together account for only about 13% of annual hospital admissions.5 Unsustainable cost pressures within the healthcare industry are leading to structural shifts, accelerating consolidation, a trend that lends well to investors’ efforts to create and leverage scale to unlock value-creation opportunities (e.g., centralization of back-office resources, improved supplier negotiations, increased patient volumes, and risk-based arrangements with managed care payers).

Conditions favor new business models.

Changing consumer preferences and pressures to reduce the total cost of care have led to service delivery innovations. One of the factors that has helped prompt these changes is regulatory: between 2013 and 2017, the Centers for Medicare and Medicaid Services increased reimbursement by 1% to 2% per annum for hospital-based surgical care but by 4% to 5% annually for similar procedures performed in ambulatory surgery centers.6 7 Additionally, technological advancements have made services and technology companies the fastest-growing profit pool in the healthcare industry.8

Access to investable platforms remains.

Fragmentation has also created investment opportunities. For example, ambulatory networks with less than 10 sites have EBITDA multiples in the low single digits, while some networks with more than 50 sites (e.g., a few large, metropolitan urgent care networks) have multiples in the low- to mid-teens. (Such large networks are still relatively rare in the healthcare services industry, however.) Furthermore, there has been a steady supply of new assets every year. VC firms have developed a significant pipeline, investing at least $20 billion in nearly 1,000 companies over the past five years.

Where has the activity been and where might it go?

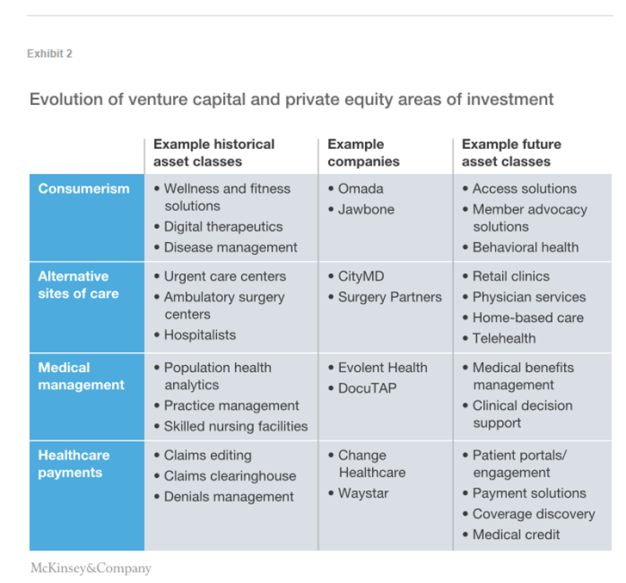
The question is not if institutional investments will continue, but rather where the money will be invested and what it will influence. We believe that the overarching focus in the next few years is likely to be on lowering the cost of care and reducing leakage in providers’ revenues. Healthcare services areas of interest are likely to be consumerism, alternative sites of care, medical management, and healthcare payments (Exhibit 2). However, the types of investment made within these areas will probably shift as industry dynamics continue to change, investors’ savvy in predicting service uptake increases, and investors become better advisors to the operators of the companies they invest in.
McKin3

Consumerism
The profile of healthcare consumers has evolved in recent years—they are now more price sensitive and tech savvy, and put greater emphasis on convenience. In our 2017 Consumer Health Insights Survey, for example, 65% of commercial insurance respondents selected cost as a top area to better under­stand when choosing where to get healthcare, and 71% said they would use video or online doctor visits if such tools were offered by their primary care physician.9 We believe this evolution will continue.

Many investor bets on consumer-centric healthcare were initially placed on wellness and disease management solutions given to consumers via their healthcare provider or employer. However, these approaches failed to gain significant traction, given the fragmented care environment and their inability to demonstrate outcome improvements sufficient to justify their cost. In the future, we believe investments in consumerism will focus more on solutions that address under­-served types of care or enable a more seamless patient experience. Most of these solutions will be geared to payers, providers, or employers—not patients—as buyers; more time is likely to be needed to document the improvements necessary to convince consumers to purchase the solutions.

Outpatient behavioral health is an example of a consumer-driven, unmet need. Future investments in behavioral health could focus on outpatient offerings (e.g., addiction clinics) or innovative solutions that integrate similar offerings with technology-enabled delivery to provide services to high-cost and/or high-risk populations. Quartet, for example, has begun to partner with health systems and payers alike to address high-need patients.

Alternatives in the provision of care

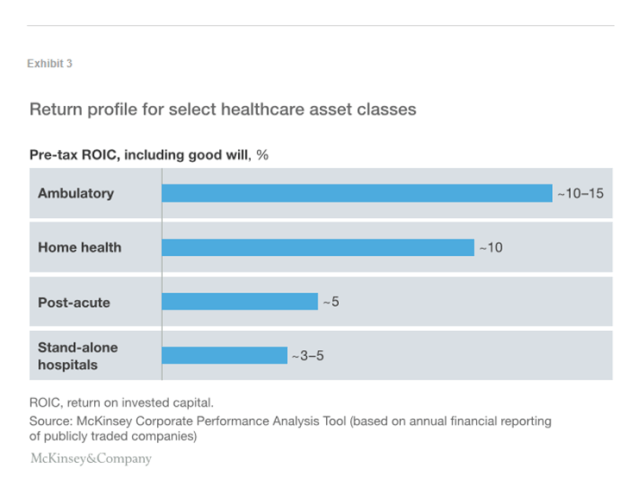
Increasingly, substitution is occurring in the provision of care—who provides it and where it is delivered. Shifts across asset classes have been driven by several forces: changes in reimbursement that favor lower-cost sites, health plan redesign to incentivize consumers to utilize lower-cost care settings (e.g., urgent care in ambulatory settings rather than hospitals; post-acute home health rather than facility-based care). Substitution within an asset class has largely focused on hospitals—cost and quality pressures have resulted in changes to the traditional business model. Many facilities, for example, have moved to outsourced hospital-based physicians (e.g., anesthesiologists and emergency physicians). The substitution effect, coupled with the newer asset classes’ better return on capital (Exhibit 3), has increased investors’ interest in two areas in particular:

Low-cost providers in need of capital to scale. Since 2012, PE investments in this area have increased by about 16% per annum. Examples include Warburg Pincus’s investment in CityMD; TPG’s in GoHealth; and Welsh, Carson, Anderson & Stowe’s in InnovAge. In these cases, the assets required capital to further scale locally or nationally. The continued emphasis on shifting to lower-cost providers will create ongoing opportunities for investment in retail-type care provision models (e.g., on-­site employer clinics), home-­based care (e.g., home health, personal care assistance), and remote health (e.g., e-visits, telehealth).

Physician groups that can provide care within alternate settings. Historically, investors have focused on hospital-based specialties that can be outsourced as a low-cost alternative to hospitals or specialties with higher exposure to private pay (e.g., dermatology). Looking forward, an increasing volume of investments will likely be made in areas that can deliver more convenient, lower-cost services for an aging population (e.g., orthopedics, gastroenterology, cardiovascular, oncology), especially given current dynamics within physician services. (The United States is projected to have a physician deficit of up to 88,000 providers by 2025.10 ) While these specialties have greater exposure to Medicare reimbursement, they also enable investors to access non-traditional value-creation levers. These levers include expanding ancillary offerings to shift day surgeries, imaging, and lab services from hospital-outpatient to free-standing settings; adopting risk-based arrangements to capture upside from managing the total cost of care; and investing in technology solutions to increase physician productivity and lower administrative burdens.
McKin4Medical management
Historically, investments in medical management focused on population health analytics and direct ownership of the parts of the care continuum that were driving variation in costs. However, success has been difficult to achieve in these areas—population health analytics predicated on risk-based arrangements with downside risk (to align incentives) and payer-provider data integration are still in nascent stages of development. Achieving success in direct ownership of skilled nursing facilities, for example, requires business model trans­formation to unlock value, given reimbursement headwinds. To date, most investors have not had sufficient operational savvy to accomplish that.

In the future, reducing medical “waste” is likely to remain a priority. Many investments may therefore focus on data-driven services that might decrease utilization and improve unit­-cost management. For example, investors will continue to help expand the historical success pharmacy benefits management achieved into other categories of benefits (e.g., medical oncology, post-acute care) and to specific types of patients (e.g., high-risk, behavioral). Nearly $1 billion in VC funding has already been in­vested in medical benefits management, which has created a pipeline of assets for PE firms.

As value-based care models continue to be implemented across the country, the need for clinical decision-support tools designed to reduce the cost of care and outcomes variability will grow. Although PE groups have yet to invest seriously in this area, decision-support companies have received more than $2 billion in VC funding since 2011—so uptake may be expected.

Optimizing healthcare payments

Each year, more than $3.5 trillion flows through the US healthcare system to providers. Employers and government are responsible for over 85% of these funds via payments to health insurers or directly to providers, but more than $200 billion is sent directly from consumers to providers.11 Given these sums, many investments have focused on the digitization and standardization of both payers’ payment integrity and providers’ revenue cycle management. However, the complexity of healthcare payments is increasing. As consumers take on a greater share of healthcare payments, it is becoming increasingly important that they be given an accurate estimate of the costs that will be billed to them before an encounter with a provider. Furthermore, “smarter” methods to predict and adjudicate payments are needed to account for risk- and quality-adjustment factors.12

Better approaches to payment are required if patients are to proactively manage out-of-pocket expenses, providers are to reduce consumer bad debt, and payers are to accurately anticipate medical expenses. For exam­ple, an integrated solution could give patients financial planning tools and an accurate idea of what their out-of-pocket costs are likely to be (based on their coverage), while also giving providers a way to estimate patients’ payments. If then combined with an online payment portal, the solution could reduce the complexity patients’ face with managing healthcare payments. New approaches might also include technology-enabled solutions that address pain points healthcare providers have in revenue cycle management, such as cover­age discovery and point-of-service payment collections.

Investors are therefore likely to continue seeking new payment solutions, with a heightened focus on those that could fundamentally change how patients, providers, and payers understand and manage payments before an encounter. Investments will probably also accelerate for technology-based solutions that enable automated eligibility checks, cost and propensity-to-pay estimation, and point-of-service payment. More than $5 million in VC funding has already supported development of several patient payment companies.

How could these trends reshape the industry?

Deal activity is likely to accelerate, given average annual returns above 10% in healthcare services.13 The inflow of capital from institutional investors will make possible the development of new business models. This inflow, in combination with greater maturity in analytics and digital capabilities, wider implementation of risk-based reimbursement arrangements, and greater pressure from payers and consumers, could accelerate the pace of change in healthcare services. Areas of the value chain that could be disrupted include both the non­-acute and post-acute care continuums, services analytics platforms, and care delivery operating models. The disruption could play out in at least six ways:

Healthcare as a service industry. Increased access to lower-cost settings of care and investments in consumerism could change thinking about how healthcare should be delivered. Healthcare could shift away from a “build it and they will come” mind­-set and toward assumptions in other services industries, where anticipating customers’ needs, digital marketing, and consumer shopping are essential.

Chronic disease management that works. The strategy of establishing standardized clinical pathways has lacked the intensity needed to drive behavioral change. New strategies based on redesigned incentives could use digital approaches to keep patients, providers, and payers more closely engaged with each other. For example, some of the top US payers are now offering members access to cellular-phone-connected glucose monitoring that issues an alert if a patient’s blood glucose is too low.

Automation that changes the cost of care. Capability improvements could make it possible to apply advanced analytics and automation to clinical and operational workflows to increase asset utilization, reduce clinical variability, and streamline labor-intensive processes. Integration of analytics into existing clinical information systems is a key opportunity to be unlocked. The need to better control the cost of care delivery positions the market for faster adoption of effective solutions.

New approaches for post-acute care. The traditional “buy it and fix it” approach that many institutional investors have used for post-acute care has proved that it is not sufficient to simply develop a more efficient version of the same business model. Given the demands for “aging in place” from consumers and lower post-acute costs from payers, effective home health and remote monitoring solutions could disrupt the market. Should this occur, the facility-based post-acute market will need to further restructure.

Carve-­out of elective ancillary revenues from hospitals. Investments are expanding from primary care groups to specialist and multi­-specialty groups that own ambulatory surgery and other ancillary facilities (e.g., diagnostic imaging, lab, pharmacy, and intermediate care). This shift is likely to create physician organizations that can cater to consumers’ one-stop-shop preferences and take risk by providing lower-cost alternatives, thereby supporting payers’ efforts at medical management. As a result, referral networks for elective care could consolidate and lower-acuity elective services would continue to shift out of hospitals.

Next generation of revenue cycle innovation. A greater focus on the intersection of patients, providers, and payers in healthcare payments, coupled with predictive analytics and consumer engagement, could breathe new life into the marketplace. This change could make possible new tools that would enable payers and providers to determine and adjudicate complex claims more effectively as well as give patients a simpler payments process.

Even if only half the investments from institutional investors are successful, the resulting industry shifts could reduce variability in care delivery, optimize appropriate sites of care, and lower the overall cost of care. Over the past decade, the annual increase in national health expenditures has averaged just over 4%.14 We believe that the trend curve could be bent—it is even possible that the cost curve could become negative (temporarily, at least) if enough waste if driven out of the system.

How providers could respond

We believe that future investments will need to be more directive and have a clearer ROIC, given the amount of capital being put into healthcare. Therefore, health systems will need to think differently about their role: Will they become leaders or followers in helping shape the industry’s future? There are a few directions a health system could take, depending on its business strategy and access to capital.

Become an active investor. Some health systems may want to take the cue from institutional investors and continue to diversify their investments and sources of revenues in healthcare services. These health systems could invest to build capabilities de novo, given their expertise in local markets, or compete with institutional investors on deals. Since 2012, health systems have engaged in nearly 1,000 transactions, and those that have successfully diversified their portfolios to include high-return ancillary assets have achieved stronger performance than their peers (nearly 10% ROIC versus less than 5% for a simple hospital network).15 However, becoming an active investor requires access to capital and a willingness to divert strategic capital to new businesses with longer timelines for returns.

Partner with institutional investors. Institutional investors will continue to buy assets across the healthcare continuum, which creates a range of partnership opportunities for health systems, including joint venture structures for acquisitions, and preferred contractual relationships with PE-backed portfolio companies. Such partnerships could be mutually beneficial to both parties. Health systems would benefit from improved offerings tailored to their markets or unmet needs, as well as having access to part of the upside gains. Institutional investors would be able to scale their investments more quickly, resulting in higher value generation. However, these arrangements may be complex to manage, and there could be differences between an institutional investor’s and the health system’s expectations for returns. Additionally, for select not-for-profit health systems, there could be tension between investing in a com­munity mission (e.g., serving Medicaid patients) and investing in revenue diversification.

Wait to acquire scaled business models. Over several years, institutional investors could potentially aggregate assets and create platforms of scale. These platforms might be attractive acquisition targets for health systems that want to accelerate their business model evolution with less risk. Health systems that want to use this approach would have to be able to afford a premium, given that PE buying sprees create scale and often result in a shortage of supply, which expands multiples. The increase in costs likely helps explain why health system acquisition activity has cooled off recently (there were only about 100 transactions in 2017, compared with about 230 two years earlier). Another drawback is that this approach requires health systems to wait and may create a window for new entrants, (e.g., payers) to acquire health­care services assets.

Health systems will also need to put defensive strategies in place. The new business models likely to emerge from institutional investments will probably continue the longer-term trend of reducing care delivery in hospitals. This will disproportionately affect health systems with high cost structures, insufficient quality out­comes, and/or an inadequate consumer experience. Furthermore, the scale­-up of non­-hospital services will decrease health systems’ negotiating leverage (e.g., with an existing anesthesiology group or revenue cycle management vendor)—a problem that will be particularly acute for smaller health systems. These pressures will increase the imperative for health systems to continue to evolve their business models to focus on delivering high-quality healthcare, to make sure their operating models have a dual focus on cost management and quality and to build capabilities to integrate with new healthcare services partners into an ecosystem to create value.

The silent shapers of healthcare are here to stay. Their investments are likely to accelerate and have even deeper impact. We believe it is crucial that health systems not attempt to maintain the status quo or be passive observers of market restructuring. The longer a health system waits to become part of the industry’s changes, the costlier the impact will be—its current business model could further erode, and entering new markets will likely become more expensive.

New, proactive tactics are needed regardless of the degree of active investment. Such an approach will allow health systems not only to preserve economics and share the market with institutional investors, but also to shape how and where care is delivered to patients.

About the author(s)
Neha Patel is a partner in McKinsey’s New Jersey office. Lisa Foo is an associate partner in the San Francisco office. Saum Sutaria, MD is a senior partner in the Silicon Valley office.

The authors would like to thank Prashanth Reddy, Nick Petersdorf, Lara Sanfilippo, Manuel Valverde, and Ellen Rosen for their support and assistance in preparing this article.
Article link: https://www.mckinsey.com/industries/healthcare-systems-and-services/our-insights/the-silent-shapers-of-healthcare-services

Navy surgeon general discusses DHA transition – health.mil

Posted by timmreardon on 12/04/2018
Posted in: Uncategorized. Leave a comment


https://health.mil/News/Articles/2018/12/03/Navy-surgeon-general-discusses-DHA-transition

Vice Adm. Forrest Faison, Navy surgeon general and chief, U.S. Navy Bureau of Medicine and Surgery, spoke about the future of Navy Medicine with military and civilian medical professionals Nov. 29 during the 127th Annual AMSUS Meeting for Federal Health Professionals at the Gaylord National Resort and Convention Center, Maryland.

NATIONAL HARBOR, Md. — On Thursday, Nov. 29, Vice Adm. Forrest Faison, Navy surgeon general and chief, U.S. Navy of Bureau of Medicine and Surgery came together with military medicine leaders during AMSUS for a panel discussion on the future of the services as they begin to transition medical facilities to the Defense Health Agency.

On Oct. 1, 2018 Navy Medicine began phase one of the DHA transition, transferring Naval Hospital Jacksonville administration, management and control to the DHA. While this transition presents significant change for Navy Medicine, the mission to keep Sailors, Marines and their families healthy and ready does not.

“The Navy is taking advantage of the many opportunities that come with this transformation. It allows us to focus on our true north and ensure we’re doing all we can to save lives and return sons and daughters home to their families” said Faison.

Several transition initiatives and milestones were shared by the services, yet the recurring theme throughout the panel’s discussion revolved around the importance of readiness.

Faison went on to describe the unique ways in which Navy Medicine is supporting the transition and taking steps to maintain readiness as hospitals and clinics transition administration, management and control to the DHA. For patients, these reforms should have little or no effect on their experience, facility and physicians. Coverage will remain the same, and patients will continue to receive the same exceptional level of care and service.

“We are focused on a future of design, not default,” said Faison. To complement changes in the organizational construct of the DHA, Navy Medicine will establish Readiness and Training Commands that support the Navy’s mission and the DHA’s role of administration and management of the MTFs.

“The Navy Medicine Readiness and Training Commands will focus on platform readiness and training so that beneficiaries can continue to receive the same level of care,” said Faison.

While the transition itself presents a great amount of change, the evolving future of warfare and health care will also continue to drive changes in the way the Navy delivers care. The emergence of great power competition and the growing capabilities of near-peer competitors to project seapower could indicate the next war at sea.

“If you’re going to fight tonight, you’ve got to be able to save lives tonight,” Faison said. “Every mom and dad in America is depending on us to do that.”

As the transition continues and the warfighting environment evolves, Navy Medicine will adapt and provide the necessary functions and capabilities needed to fight the next fight, whether it be on sea, land or in the air.

Disclaimer: Re-published content may have been edited for length and clarity.Read original post.

Social Determinants Of Health: Holy Grail Or Dead-End Road? – Forbes

Posted by timmreardon on 12/03/2018
Posted in: Uncategorized. Leave a comment

Lisa Fitzpatrick Contributor

Forbesxx1

Food establishment, Southeast Washington, DCLisa K. Fitzpatrick, MD
At the 2018 Milken Institute Future of Health Summit, Congressman Bill Cassidy said, “Obesity is often linked to social determinants that have nothing to do with food.” To bolster the point he shared a hypothetical but realistic example of family living in a food desert and relying on public transportation to and from the grocery store. While unfathomable for many health care leaders, policymakers and investors, transporting multiple grocery bags on public transportation is a cultural norm for many of the nation’s poor. Lack of convenient access to healthy food is among the social determinants of health (SDH) now so feverishly discussed as if they were the Holy Grail for improving health outcomes among the poor. While SDH must be considered in devising health care interventions, findings from our qualitative research study funded by the Commonwealth Fund* suggest incorporation of SDH as a strategy to improve health outcomes are unlikely to be successful without concomitant long-term commitment to addressing a few social and cultural challenges.
First, food literacy is low. Participants understood the link between food and good health and expressed interest in learning more about healthy food. A conversation about food with one participant led to a discussion about her inability to identify an eggplant or distinguish a zucchini from a cucumber. She is not alone. Therefore, consistent and sustainable food education is essential. This includes identification of foods, reading and understanding food labels and skills development to prepare meals. Also, modifying food-related policies to facilitate access is a critical step but the impact of these changes will only be realized if we also shift the food culture and perspectives about healthy food relative to the food choices persistently available in poor communities. For example, a few participants discussed their preferences for fast food and carry out options over fresh fruits and vegetables. These preferences were linked to flavor rather than cost. Thus, although improving access to conveniently located healthy food is imperative for good health, community-wide adoption of healthy food choices will require a gradual shift in the community’s palate and a change in the way low-income communities think about and value food.
Second, transportation benefits are vital but can’t replace trust. One of the most tangible and measurable SDH-related interventions is improving access to transportation. In many primary care clinics serving the poor, the no-show rates are persistently high and these missed appointments are often reportedly due to lack of transportation. To address this challenge, many health systems and insurance carriers now provide non-emergency medical transportation to health care visits. However, the participants who discussed transportation benefits suggested that often the reasons for not keeping appointments have little to do with transportation and that if they felt the visit was essential, they could identify options for attending health care visits. Some shared negative experiences with the health care system and reported the single biggest determinant of returning for follow-up was the relationship with the provider and the health system environment. Several participants shared experiences they perceived as disrespectful, unwelcoming, judgmental and condescending. One participant said, “People don’t care about you if you are poor and [they] won’t give you the best treatment.” Among Hispanic participants, trust was named as a powerful predictor of consistent engagement in health care.

Finally, poverty and lack of economic opportunity are driving health inequities. Overall, many people were disengaged from their health and the health care system because their economic survival was in constant competition with what they perceived as non-immediate threats like health. Both black and Hispanic participants shared examples highlighting how lack of job and financial security forced them to delay health care needs. One participant described delaying medical evaluation for a shoulder injury for seven months because a missed day of work meant lost opportunity for future work because he would immediately be replaced by another worker. For the poor, desperate financial need clouds the ability to prioritize health, particularly when most preventable health conditions are often intangible and thus perceived as non-threatening. The need to address financial security as a means to achieve better health outcomes is increasingly recognized and has led to a movement exploring medical financial partnerships. These partnerships explore integration of SDH with financial empowerment interventions. The approach is a new paradigm for the US but is poised to revolutionize the delivery of social, financial and medical integration of service delivery.
Integrating SDH interventions into healthcare delivery is likely to nudge some individual health outcomes. However, recent and pervasive discussions about SDH suggest a belief among many that they are the Holy Grail for achieving the long-sought but elusive health outcomes for low-income populations. These discussions with study participants suggest a need to further evaluate proposed approaches for and expectations from burgeoning SDH interventions. Achieving population-based shifts in health outcomes for low-income communities requires moving far beyond text message reminders, Uber rides to clinic visits and vouchers for farmer’s markets and food pantries. These shifts demand bold and transformative steps to address poverty by providing education, economic opportunity and a pathway to lifelong economic stability. Congressman Bill Cassidy also said, “Prosperity is the key to improving health outcomes”. As we develop interventions for the social determinants of health, unless we begin to heed this message, in the years ahead rather than finding the Holy Grail, we will instead certainly find ourselves on the path to a dead-end road.

Article link: https://www.forbes.com/sites/lisafitzpatrick/2018/11/02/social-determinants-of-health-holy-grail-or-dead-end-road/#76d0265d649c

Strategy on Reducing Regulatory and Administrative Burden Relating to the Use of Health IT and EHRs – Draft for Public Comment – HHS

Posted by timmreardon on 11/28/2018
Posted in: Uncategorized. Leave a comment

Read Report

HHS-ONC1

HHS wants to simplify electronic health record requirements – Federal Times

Posted by timmreardon on 11/28/2018
Posted in: Uncategorized. Leave a comment

By: Jessie Bur

FedTimes-1

Technology is supposed to make the health care process easier and more efficient, but regulatory and administrative requirements mean that health care professionals are spending too much time and effort entering data into electronic health records systems, according to a draft Department of Health and Human Services strategy.


The new EHR strategy, released for public comment Nov. 28, proposes to reduce health care provider burden with EHRs by fixing regulatory requirements.


“Usable, interoperable health IT was one of the first elements of the vision I laid out earlier this year for transforming our health system into one that pays for value,” said HHS Secretary Alex Azar.


“With the significant growth in EHRs comes frustration caused, in many cases, by regulatory and administrative requirements stacked on top of one another. Addressing the challenge of health IT burden and making EHRs useful for patients and providers, as the solutions in this draft report aim to do, will help pave the way for value-based transformation.”


The strategy proposes three goals for improving EHR usage:

  1. Reduce the effort and time required to record health information in EHRs for clinicians;
  2. Reduce the effort and time required to meet regulatory reporting requirements for clinicians, hospitals and health care organizations; and
  3. Improve the functionality and intuitiveness (ease of use) of EHRs.

“Information technology has automated processes in every industry except health care, where the introduction of EHRs resulted in additional burden on clinicians,” said Don Rucker, national coordinator for health information technology.

“Health IT tools need to be intuitive and functional so that clinicians can focus on their patients and not documentation. This draft strategy identifies ways the government and private sector can alleviate burden. I look forward to input from the public to improve this strategy.”

The strategy proposes a number of actions, including reducing the regulatory burden around patient visits, standardizing data and processes for EHRs, simplifying EHR reporting program requirements and doing an inventory of reporting requirements across federal programs to help reduce the reporting burden on clinicians and providers.

The strategy was led by the HHS Office of the National Coordinator for Health Information Technology, in partnership with the Centers for Medicare and Medicaid Services and developed through consultation with clinicians themselves.

“Over the past year, we hosted listening sessions, received written feedback, and heard from a wide range of clinical stakeholders about the current health IT systems and the requirements specifying documentation, reimbursement and quality reporting that are burdensome and should be re-examined,” said Seema Verma, CMS administrator.

“CMS has demonstrated through bold regulatory action the importance of reducing clinician burden.”

Those interested in commenting on the strategy have until Jan. 28, 2019.

Article link: https://www.federaltimes.com/it-networks/health-it/2018/11/28/hhs-wants-to-simplify-electronic-health-record-requirements/

Posts navigation

← Older Entries
Newer Entries →
  • Search site

  • Follow healthcarereimagined on WordPress.com
  • Recent Posts

    • By Barring Profits on Basic Coverage, Switzerland Keeps Insurers from Denying Care – Commonwealth Fund 10/19/2026
    • Patients’ Perspectives on AI in Primary Care – Commonwealth Fund 09/11/2026
    • Bitcoin Mining Energy Footprint 08/06/2026
    • Closing the AI Hype Gap 08/05/2026
    • Why Artificial Intelligence is Neither Artificial, Nor Intelligent 07/31/2026
    • Agentic AI, explained 07/05/2026
    • Heeding the pope’s call to ensure AI protects human dignity – MIT Sloan Management 06/01/2026
    • Association between Wealth and Mortality in the United States and Europe – New England Journal of Medicine 05/30/2026
    • U.S. Health Care from a Global Perspective, 2026 – The Commonwealth Fund 05/30/2026
    • Anthropic co-founder Chris Olah’s remarks on Pope Leo XIV’s encyclical “Magnifica humanitas” 05/28/2026
  • Categories

    • Accountable Care Organizations
    • ACOs
    • AHRQ
    • American Board of Internal Medicine
    • Big Data
    • Blue Button
    • Board Certification
    • Cancer Treatment
    • Data Science
    • Digital Services Playbook
    • DoD
    • EHR Interoperability
    • EHR Usability
    • Emergency Medicine
    • FDA
    • FDASIA
    • GAO Reports
    • Genetic Data
    • Genetic Research
    • Genomic Data
    • Global Standards
    • Health Care Costs
    • Health Care Economics
    • Health IT adoption
    • Health Outcomes
    • Healthcare Delivery
    • Healthcare Informatics
    • Healthcare Outcomes
    • Healthcare Security
    • Helathcare Delivery
    • HHS
    • HIPAA
    • ICD-10
    • Innovation
    • Integrated Electronic Health Records
    • IT Acquisition
    • JASONS
    • Lab Report Access
    • Military Health System Reform
    • Mobile Health
    • Mobile Healthcare
    • National Health IT System
    • NSF
    • ONC Reports to Congress
    • Oncology
    • Open Data
    • Patient Centered Medical Home
    • Patient Portals
    • PCMH
    • Precision Medicine
    • Primary Care
    • Public Health
    • Quadruple Aim
    • Quality Measures
    • Rehab Medicine
    • TechFAR Handbook
    • Triple Aim
    • U.S. Air Force Medicine
    • U.S. Army
    • U.S. Army Medicine
    • U.S. Navy Medicine
    • U.S. Surgeon General
    • Uncategorized
    • Value-based Care
    • Veterans Affairs
    • Warrior Transistion Units
    • XPRIZE
  • Archives

    • October 2026 (1)
    • September 2026 (1)
    • August 2026 (2)
    • July 2026 (2)
    • June 2026 (1)
    • May 2026 (12)
    • April 2026 (4)
    • March 2026 (9)
    • February 2026 (6)
    • January 2026 (8)
    • December 2025 (11)
    • November 2025 (9)
    • October 2025 (10)
    • September 2025 (4)
    • August 2025 (7)
    • July 2025 (2)
    • June 2025 (9)
    • May 2025 (4)
    • April 2025 (11)
    • March 2025 (11)
    • February 2025 (10)
    • January 2025 (12)
    • December 2024 (12)
    • November 2024 (7)
    • October 2024 (5)
    • September 2024 (9)
    • August 2024 (10)
    • July 2024 (13)
    • June 2024 (18)
    • May 2024 (10)
    • April 2024 (19)
    • March 2024 (35)
    • February 2024 (23)
    • January 2024 (16)
    • December 2023 (22)
    • November 2023 (38)
    • October 2023 (24)
    • September 2023 (24)
    • August 2023 (34)
    • July 2023 (33)
    • June 2023 (30)
    • May 2023 (35)
    • April 2023 (30)
    • March 2023 (30)
    • February 2023 (15)
    • January 2023 (17)
    • December 2022 (10)
    • November 2022 (7)
    • October 2022 (22)
    • September 2022 (16)
    • August 2022 (33)
    • July 2022 (28)
    • June 2022 (42)
    • May 2022 (53)
    • April 2022 (35)
    • March 2022 (37)
    • February 2022 (21)
    • January 2022 (28)
    • December 2021 (23)
    • November 2021 (12)
    • October 2021 (10)
    • September 2021 (4)
    • August 2021 (4)
    • July 2021 (4)
    • May 2021 (3)
    • April 2021 (1)
    • March 2021 (2)
    • February 2021 (1)
    • January 2021 (4)
    • December 2020 (7)
    • November 2020 (2)
    • October 2020 (4)
    • September 2020 (7)
    • August 2020 (11)
    • July 2020 (3)
    • June 2020 (5)
    • April 2020 (3)
    • March 2020 (1)
    • February 2020 (1)
    • January 2020 (2)
    • December 2019 (2)
    • November 2019 (1)
    • September 2019 (4)
    • August 2019 (3)
    • July 2019 (5)
    • June 2019 (10)
    • May 2019 (8)
    • April 2019 (6)
    • March 2019 (7)
    • February 2019 (17)
    • January 2019 (14)
    • December 2018 (10)
    • November 2018 (20)
    • October 2018 (14)
    • September 2018 (27)
    • August 2018 (19)
    • July 2018 (16)
    • June 2018 (18)
    • May 2018 (28)
    • April 2018 (3)
    • March 2018 (11)
    • February 2018 (5)
    • January 2018 (10)
    • December 2017 (20)
    • November 2017 (30)
    • October 2017 (33)
    • September 2017 (11)
    • August 2017 (13)
    • July 2017 (9)
    • June 2017 (8)
    • May 2017 (9)
    • April 2017 (4)
    • March 2017 (12)
    • December 2016 (3)
    • September 2016 (4)
    • August 2016 (1)
    • July 2016 (7)
    • June 2016 (7)
    • April 2016 (4)
    • March 2016 (7)
    • February 2016 (1)
    • January 2016 (3)
    • November 2015 (3)
    • October 2015 (2)
    • September 2015 (9)
    • August 2015 (6)
    • June 2015 (5)
    • May 2015 (6)
    • April 2015 (3)
    • March 2015 (16)
    • February 2015 (10)
    • January 2015 (16)
    • December 2014 (9)
    • November 2014 (7)
    • October 2014 (21)
    • September 2014 (8)
    • August 2014 (9)
    • July 2014 (7)
    • June 2014 (5)
    • May 2014 (8)
    • April 2014 (19)
    • March 2014 (8)
    • February 2014 (9)
    • January 2014 (31)
    • December 2013 (23)
    • November 2013 (48)
    • October 2013 (25)
  • Tags

    Business Defense Department Department of Veterans Affairs EHealth EHR Electronic health record Food and Drug Administration Health Health informatics Health Information Exchange Health information technology Health system HIE Hospital IBM Mayo Clinic Medicare Medicine Military Health System Patient Patient portal Patient Protection and Affordable Care Act United States United States Department of Defense United States Department of Veterans Affairs
  • Upcoming Events

Blog at WordPress.com.
healthcarereimagined
Blog at WordPress.com.
  • Subscribe Subscribed
    healthcarereimagined
    Join 149 other subscribers

    Have a WordPress.com account? Log in now.

  • healthcarereimagined
    View site in Reader
    Manage subscriptionsSign upLog in
    Report this content
    Collapse this bar
Loading Comments...